 |
Atlas H&E-TME: Scalable AI-Based Tissue Profiling at Expert Pathologist-Level Accuracy
Hematoxylin and eosin staining is the cornerstone of histopathology, but extracting scalable, quantitative data from these whole slide images remains a central challenge in computational pathology.
When evaluating whether an AI model accurately profiles a tumor's microenvironment, researchers face a structural roadblock. Validating against standard H&E slides is limited by morphological ambiguity and high inter-rater variability among pathologists. Conversely, using precise molecular stains like immunohistochemistry (IHC) creates a highly reliable reference, but the cost and complexity make it difficult to scale across massive validation cohorts.
A new paper by 𝙆𝙖𝙞 𝙎𝙩𝙖𝙣𝙙𝙫𝙤𝙨𝙨 𝙚𝙩 𝙖𝙡. addresses this exact tension by introducing a dual validation framework alongside their comprehensive tissue profiling system,
𝘼𝙩𝙡𝙖𝙨 𝙃&𝙀-𝙏𝙈𝙀.
Here are the key innovations detailed in their research:
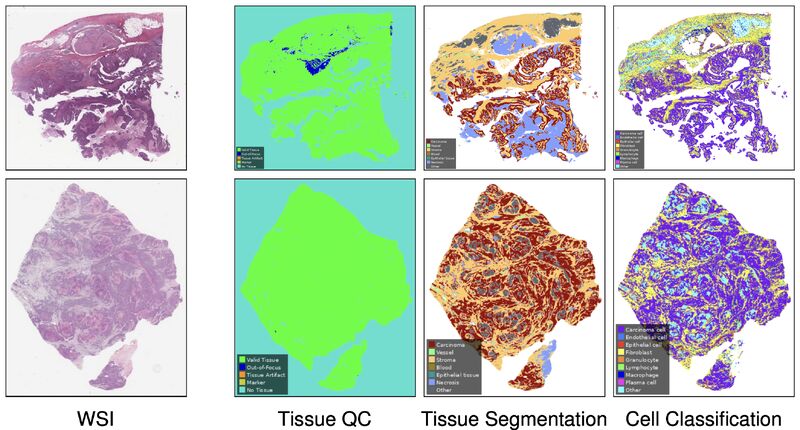
• 𝙏𝙝𝙚 𝙈𝙤𝙙𝙚𝙡: Built on the Atlas family of pathology foundation models, the system predicts tissue quality, tissue segmentation, and cell types across multiple cancer types. It generates over 4,500 quantitative readouts per slide at cell-level resolution, capturing spatial relationships and neighborhood features.
• 𝙄𝙣-𝘿𝙚𝙥𝙩𝙝 𝙑𝙖𝙡𝙞𝙙𝙖𝙩𝙞𝙤𝙣: To establish a biologically grounded truth, the authors used a sequential bleach-and-restain workflow. They first scanned sections with H&E, then bleached and restained the exact same physical sections with a 5-plex IHC panel. This approach substantially improved inter-rater agreement, particularly for ambiguous immune cells like macrophages, granulocytes, and plasma cells. When benchmarked against this molecularly grounded consensus, 𝘼𝙩𝙡𝙖𝙨 𝙃&𝙀-𝙏𝙈𝙀 matched or exceeded the cell classification performance of board-certified pathologists working from H&E alone.
• 𝙄𝙣-𝘽𝙧𝙚𝙖𝙙𝙩𝙝 𝙑𝙖𝙡𝙞𝙙𝙖𝙩𝙞𝙤𝙣: To test true generalizability, the model was evaluated on over 200,000 high-confidence H&E annotations spanning more than 1,500 cases. The cohort covered eight primary cancer types and their five most common metastatic sites, drawing from over 25 sources and 8 different scanner models. Across this massive morphological and technical scope, the model demonstrated robust and consistent performance.
𝙏𝙝𝙚 𝙏𝙖𝙠𝙚𝙖𝙬𝙖𝙮: By combining biological depth with morphological breadth in its validation, this framework turns the ubiquitous H&E slide into a reliable, quantitative window into the tumor microenvironment without needing to stain for every biomarker.
|
|
|
|
|
 |
Do Foundation Models See Biology? Evaluating Attention Coherence with Spatial Transcriptomics in Glioblastoma
Attention-based multiple instance learning maps are widely used to assign spatial weights to tissue patches and explain slide-level predictions in computational pathology. But whether these attention weights reflect genuine biological mechanisms or merely uninterpretable visual artifacts remains debated.
In digital pathology, biological evaluation of attention maps is almost universally performed through qualitative pathologist review. While valuable, this manual approach is subjective, prone to inter-rater variability, and unable to scale to large benchmark datasets.
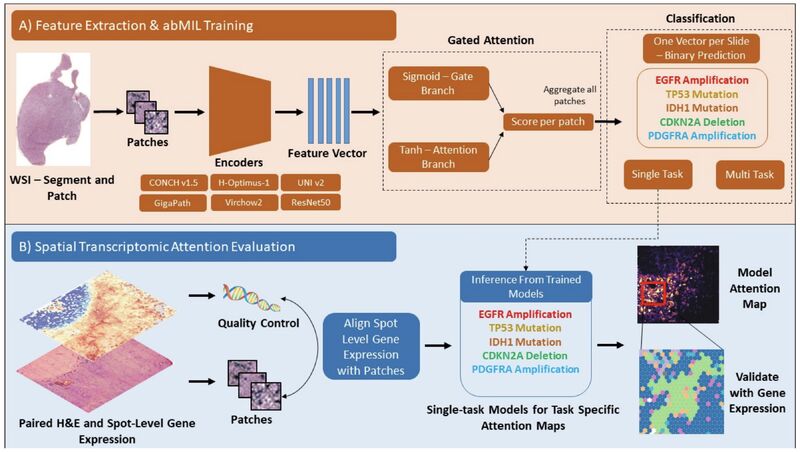
A new study by 𝘿𝙞𝙡𝙖𝙠𝙨𝙝𝙖𝙣 𝙎𝙧𝙞𝙠𝙖𝙣𝙩𝙝𝙖𝙣 𝙚𝙩 𝙖𝙡. addresses this limitation by introducing an orthogonal, hypothesis-free framework that uses co-registered Visium spatial transcriptomics (~69,000 spots across 18 glioblastoma samples) to quantitatively evaluate attention maps. They evaluated five pathology foundation models alongside a ResNet50 baseline.
Here are the key findings detailed in their research:
• 𝘼𝙩𝙩𝙚𝙣𝙩𝙞𝙤𝙣 𝘾𝙖𝙥𝙩𝙪𝙧𝙚𝙨 𝙈𝙪𝙡𝙩𝙞-𝙂𝙚𝙣𝙚 𝙋𝙧𝙤𝙜𝙧𝙖𝙢𝙨: Rather than spotlighting individual gene mutations, attention
maps correlate with coordinated transcriptional states. Enrichment followed a five-fold gradient from hallmark pathways down to individual genes, concentrating primarily in metabolic and proliferative tumor cell regions.
• 𝙎𝙥𝙖𝙩𝙞𝙖𝙡 𝙎𝙢𝙤𝙤𝙩𝙝𝙣𝙚𝙨𝙨 𝘿𝙤𝙚𝙨 𝙉𝙤𝙩 𝙀𝙦𝙪𝙖𝙡 𝘽𝙞𝙤𝙡𝙤𝙜𝙞𝙘𝙖𝙡 𝘾𝙤𝙝𝙚𝙧𝙚𝙣𝙘𝙚: Visually appealing, contiguous attention maps do not imply biological fidelity. The ResNet50 baseline produced the most spatially smooth attention maps but showed the weakest biological enrichment. In contrast, foundation models produced less spatially contiguous maps that aligned far more strongly with underlying transcriptional programs.
• 𝙀𝙣𝙘𝙤𝙙𝙚𝙧-𝙎𝙥𝙚𝙘𝙞𝙛𝙞𝙘
𝘽𝙞𝙤𝙡𝙤𝙜𝙞𝙘𝙖𝙡 𝙋𝙧𝙚𝙛𝙚𝙧𝙚𝙣𝙘𝙚𝙨: Different foundation model encoders prioritize distinct biological compartments. For instance, GigaPath demonstrated a strong affinity for neuronal compartments, whereas H-Optimus-1 prioritized glial and mesenchymal features.
• 𝙄𝙣𝙩𝙚𝙧𝙣𝙖𝙡 𝙑𝙨. 𝙀𝙭𝙩𝙚𝙧𝙣𝙖𝙡 𝙑𝙖𝙡𝙞𝙙𝙖𝙩𝙞𝙤𝙣 𝙂𝙖𝙥𝙨: Model performance rankings established on internal cross-validation failed to hold on an independent external validation set. UNI v2 ranked fifth on internal validation but rose to first on external TCGA validation, demonstrating that single-cohort benchmarks can produce misleading encoder recommendations.
𝙏𝙝𝙚 𝙏𝙖𝙠𝙚𝙖𝙬𝙖𝙮: Evaluating computational pathology models requires moving beyond qualitative visual inspection. Grounding attention maps in spatial transcriptomics provides a quantitative, objective framework to determine what foundation models learn from tissue morphology.
|
|
|
|
|
 |
General-purpose large language models outperform specialized clinical AI tools on medical benchmarks
Specialized clinical AI tools have entered medical practice with promises of superior performance driven by domain-specific training or retrieval-augmented generation (RAG). But when put to an independent, blinded test by practicing physicians, do they actually outperform general frontier LLMs?
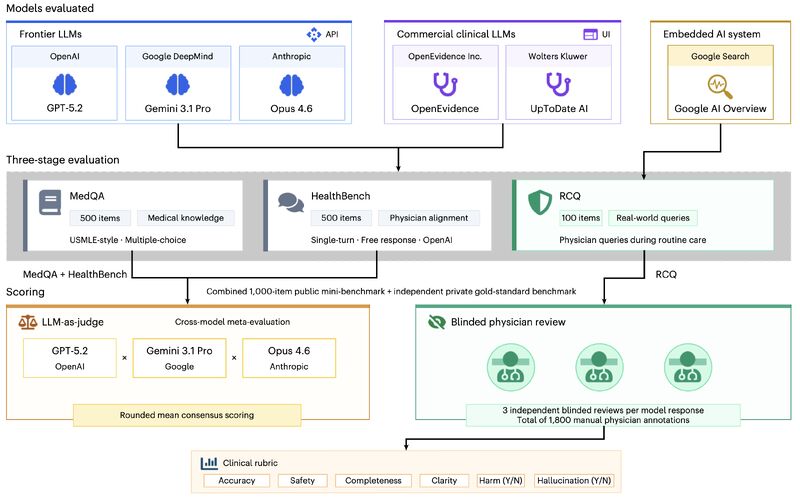
A study published in 𝙉𝙖𝙩𝙪𝙧𝙚 𝙈𝙚𝙙𝙞𝙘𝙞𝙣𝙚 by 𝙆𝙧𝙞𝙩𝙝𝙞𝙠 𝙑𝙞𝙨𝙝𝙬𝙖𝙣𝙖𝙩𝙝 𝙚𝙩 𝙖𝙡. provides empirical data on this question. They evaluated two commercial clinical tools against three general-purpose frontier LLMs (GPT-5.2, Gemini 3.1 Pro, Claude Opus 4.6) and a search-embedded control across medical knowledge exams, expert alignment and real clinical queries.
𝙒𝙝𝙖𝙩
𝙏𝙝𝙚 𝙎𝙩𝙪𝙙𝙮 𝙀𝙨𝙩𝙖𝙗𝙡𝙞𝙨𝙝𝙚𝙙:
• 𝙁𝙧𝙤𝙣𝙩𝙞𝙚𝙧 𝙇𝙇𝙈𝙨 𝙇𝙚𝙖𝙙 𝙄𝙣 𝘾𝙡𝙞𝙣𝙞𝙘𝙖𝙡 𝙏𝙚𝙭𝙩: General-purpose LLMs consistently scored higher than specialized clinical tools across all three evaluation stages. On real clinical queries, specialized clinical tools performed comparably to a standard, search-embedded AI overview.
• 𝙏𝙝𝙚 𝙍𝘼𝙂 𝙇𝙞𝙢𝙞𝙩𝙖𝙩𝙞𝙤𝙣: The authors noted that RAG pipelines used by clinical tools can degrade performance when retrieved context is irrelevant or poorly integrated by the base model.
𝙈𝙮 𝙋𝙚𝙧𝙨𝙥𝙚𝙘𝙩𝙞𝙫𝙚:
•
𝙏𝙝𝙚 𝙏𝙚𝙭𝙩-𝙋𝙞𝙭𝙚𝙡 𝘼𝙨𝙮𝙢𝙢𝙚𝙩𝙧𝙮: Why does generalism win in text? Language is a universal medium. Human medical knowledge, reasoning, and clinical communication share linguistic structures with general text. A web-scale LLM learns broad causal logic and instruction-following that translate directly to medical text queries.
• 𝘿𝙤𝙢𝙖𝙞𝙣-𝙇𝙤𝙘𝙠𝙚𝙙 𝙎𝙞𝙜𝙣𝙖𝙡𝙨 𝙄𝙣 𝙄𝙢𝙖𝙜𝙞𝙣𝙜: In medical imaging, physical signals are domain-locked. Gigapixel tissue slides and 3D radiological scans share virtually zero statistical distribution or feature spaces with natural web images. Pre-training on web photos does not teach a model to identify nuclear pleomorphism or complex spatial microenvironments.
• 𝙏𝙖𝙨𝙠 𝙂𝙧𝙖𝙣𝙪𝙡𝙖𝙧𝙞𝙩𝙮: While text queries often operate at a coarse-to-medium level where broad LLM reasoning excels, computational pathology requires sub-micron, fine-grained analysis of cellular architecture. This level of precision demands purpose-built biological
foundation models and specialized spatial encoders—not just adapted general vision models.
𝙏𝙝𝙚 𝙏𝙖𝙠𝙚𝙖𝙬𝙖𝙮: For text-based medical tasks, 𝙑𝙞𝙨𝙝𝙬𝙖𝙣𝙖𝙩𝙝 𝙚𝙩 𝙖𝙡. demonstrate that scale, alignment, and general cross-domain reasoning outweigh domain-specific tuning as determinants of medical competency.
While general reasoning conquers specialized text, I think that physical signals in medical imaging remain domain-locked—meaning purpose-built, domain-specific foundation models remain irreplaceable.
|
|
|
|
|
|
|
